See whether Helium helps you make better-informed decisions. Try every Pro Trader feature for 30 days. No credit card required.
Try every Pro Trader feature for 30 days. No credit card required.

August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed.
Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster.
·
5 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday.
At least 717 patients were in isolation while 749 patients have recovered.”
· exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
Reporting on the Ebola outbreak uses urgent language and authoritative sources while including a prominent fundraising appeal.
The Bundibugyo virus responsible has no approved treatment or vaccine; the outbreak is the second-largest on record after the 2014-2016 West Africa outbreak.
Automated analysis; not human reviewed.
Limitations: The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing.
·
8 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 5 of 8 scored dimensions.
Claim: The article uses sensational language in the headline and quotes to heighten urgency.
“Over 1,700 dead from world's fastest-spreading Ebola outbreak as WHO offers dire warning” · exact text match
“The world’s fastest-growing Ebola outbreak is now spreading at a rate that outpaces efforts to contain it” · exact text match
Why: The headline and opening sentence use superlatives like 'fastest-spreading' and 'dire warning', which are sensational but supported by factual data.
Claim: The article emphasizes alarming spread and fatal outcomes to evoke fear.
“the outbreak is still "spreading at an alarming and unprecedented rate"” · not found in supplied text
“44 were fatal” · exact text match
Why: Direct quotes and statistics highlight rapid transmission and high fatality, framing the situation as urgent and fearful.
Claim: The article relies heavily on statements from WHO, Africa CDC, and Doctors Without Borders to establish credibility.
“WHO Director-General Tedros Adhanom Ghebreyesus stated” · exact text match
“Dr. Jean Kaseya, head of the Africa Centers for Disease Control, noted” · exact text match
Why: Multiple authoritative sources are quoted without countervailing voices, but this is appropriate for a health crisis where such authorities are the primary information sources.
Claim: The article evokes negative emotions by highlighting deaths and suffering.
“attributed the deaths of his two brothers from Ebola to the strike” · exact text match
“1,751 deaths” · exact text match
Why: Personal tragedy and high death toll create a negative emotional tone, but the reporting remains largely factual.
Claim: The article is highly credible due to clear attribution and data sourcing.
“according to the latest data from Congo’s Ministry of Health” · exact text match
“He told The Associated Press” · not found in supplied text
Why: Numbers are attributed to official sources, quotes are from named individuals and organizations, and the reporting is consistent with standard journalistic practice.
Claim: The article includes a prominent fundraising paragraph promoting donations to the publisher.
“Your donation allows us to keep sending journalists to speak to both sides of the story” · exact text match
“we choose not to lock Americans out of our reporting and analysis with paywalls” · exact text match
Why: A block of text explicitly asks for donations and promotes the publisher's values, which is a form of advertising for the publication itself.
Claim: The article provides detailed, informative data on the outbreak.
“77 most recent cases reported in 24 hours, 44 were fatal” · exact text match
“at least 60 to 70 percent of new cases emerging from individuals not being monitored” · exact text match
Why: Includes specific metrics like case numbers, fatality rate, contact tracing failure rate, and funding figures, indicating depth and intelligence.
The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
Neutral factual reporting on the Ebola outbreak and WHO response, with no evident framing bias beyond straightforward attribution and data presentation.
Automated analysis; not human reviewed.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 0 of 3 scored dimensions.
Claim: The article presents facts without opinion.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: The sentence reports an event and cites a factual claim without evaluative language.
Claim: The article maintains a neutral emotional tone.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: No emotional language; factual reporting.
Claim: The article demonstrates high credibility through attribution and data.
“"according to the latest data from Congo’s Ministry of Health"” · not found in supplied text
“"Dr Jean Kaseya, Director-General of the Africa Centres for Disease Control, noted"” · not found in supplied text
Why: Multiple attributions to official sources and named experts enhance trustworthiness.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed.
Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster.
·
5 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday.
At least 717 patients were in isolation while 749 patients have recovered.”
· exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed.
Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster.
·
5 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday.
At least 717 patients were in isolation while 749 patients have recovered.”
· exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
Neutral factual reporting on the Ebola outbreak and WHO response, with no evident framing bias beyond straightforward attribution and data presentation.
Automated analysis; not human reviewed.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 0 of 3 scored dimensions.
Claim: The article presents facts without opinion.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: The sentence reports an event and cites a factual claim without evaluative language.
Claim: The article maintains a neutral emotional tone.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: No emotional language; factual reporting.
Claim: The article demonstrates high credibility through attribution and data.
“"according to the latest data from Congo’s Ministry of Health"” · not found in supplied text
“"Dr Jean Kaseya, Director-General of the Africa Centres for Disease Control, noted"” · not found in supplied text
Why: Multiple attributions to official sources and named experts enhance trustworthiness.
August 04, 2026 · 0 shares
Reliance on official WHO statements and statistical data with a neutral factual tone.
Automated analysis; not human reviewed.
Limitations: Input includes many promotional blurbs that could be mistaken for article content, but analysis focused on the main text.
·
2 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 2 scored dimensions.
Claim: The article maintains an objective framing by relying on attributed statements and numerical data.
“The World Health Organization (WHO) on Tuesday called for greater support to tackle the Ebola outbreak in the Democratic Republic of Congo (DRC), warning that the response is still struggling to keep pace with the spread of the disease.” · exact text match
“The Country has recorded 3,802 confirmed Ebola cases, including 1,707 deaths.” · exact text match
Why: The publisher presents facts and quotes without subjective commentary or emotional language.
Claim: The article demonstrates high credibility by naming specific WHO spokespersons and providing precise figures.
“WHO spokesman Tarik Jasarevic told reporters in Geneva.” · exact text match
“The Country has recorded 3,802 confirmed Ebola cases, including 1,707 deaths.” · exact text match
Why: The sources are identified and the data is specific, enhancing trustworthiness.
Input includes many promotional blurbs that could be mistaken for article content, but analysis focused on the main text.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed.
Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster.
·
5 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday.
At least 717 patients were in isolation while 749 patients have recovered.”
· exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
Reporting on the Ebola outbreak uses urgent language and authoritative sources while including a prominent fundraising appeal.
The Bundibugyo virus responsible has no approved treatment or vaccine; the outbreak is the second-largest on record after the 2014-2016 West Africa outbreak.
Automated analysis; not human reviewed.
Limitations: The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing.
·
8 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 5 of 8 scored dimensions.
Claim: The article uses sensational language in the headline and quotes to heighten urgency.
“Over 1,700 dead from world's fastest-spreading Ebola outbreak as WHO offers dire warning” · exact text match
“The world’s fastest-growing Ebola outbreak is now spreading at a rate that outpaces efforts to contain it” · exact text match
Why: The headline and opening sentence use superlatives like 'fastest-spreading' and 'dire warning', which are sensational but supported by factual data.
Claim: The article emphasizes alarming spread and fatal outcomes to evoke fear.
“the outbreak is still "spreading at an alarming and unprecedented rate"” · not found in supplied text
“44 were fatal” · exact text match
Why: Direct quotes and statistics highlight rapid transmission and high fatality, framing the situation as urgent and fearful.
Claim: The article relies heavily on statements from WHO, Africa CDC, and Doctors Without Borders to establish credibility.
“WHO Director-General Tedros Adhanom Ghebreyesus stated” · exact text match
“Dr. Jean Kaseya, head of the Africa Centers for Disease Control, noted” · exact text match
Why: Multiple authoritative sources are quoted without countervailing voices, but this is appropriate for a health crisis where such authorities are the primary information sources.
Claim: The article evokes negative emotions by highlighting deaths and suffering.
“attributed the deaths of his two brothers from Ebola to the strike” · exact text match
“1,751 deaths” · exact text match
Why: Personal tragedy and high death toll create a negative emotional tone, but the reporting remains largely factual.
Claim: The article is highly credible due to clear attribution and data sourcing.
“according to the latest data from Congo’s Ministry of Health” · exact text match
“He told The Associated Press” · not found in supplied text
Why: Numbers are attributed to official sources, quotes are from named individuals and organizations, and the reporting is consistent with standard journalistic practice.
Claim: The article includes a prominent fundraising paragraph promoting donations to the publisher.
“Your donation allows us to keep sending journalists to speak to both sides of the story” · exact text match
“we choose not to lock Americans out of our reporting and analysis with paywalls” · exact text match
Why: A block of text explicitly asks for donations and promotes the publisher's values, which is a form of advertising for the publication itself.
Claim: The article provides detailed, informative data on the outbreak.
“77 most recent cases reported in 24 hours, 44 were fatal” · exact text match
“at least 60 to 70 percent of new cases emerging from individuals not being monitored” · exact text match
Why: Includes specific metrics like case numbers, fatality rate, contact tracing failure rate, and funding figures, indicating depth and intelligence.
The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing.
August 04, 2026 · 0 shares
Straightforward reporting of a Chinese Foreign Ministry statement on Ebola support, with no editorial slant.
Automated analysis; not human reviewed.
Limitations: The article is very short and contains only a government statement; limited independent information.
·
1 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 1 of 1 scored dimensions.
Claim: The article covers a government statement, making it political in nature, but the reporting is neutral.
“Spokesperson Lin Jian made the remarks in response to a question on the third Chinese government's medical expert team arriving in Kinshasa, capital of the Democratic Republic of the Congo (DRC), on August 1.” · exact text match
Why: The article focuses on a foreign ministry spokesperson's statement about China's international support, which is inherently political content.
The article is very short and contains only a government statement; limited independent information.
August 06, 2026 · 0 shares
The report conveys urgency about the Ebola outbreak through official concerns about mutation and a planned major response escalation, while maintaining a factual, attributed tone.
Automated analysis; not human reviewed.
Limitations: The article is extremely brief, limiting the depth of evidence for bias classification.
·
9 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 7 of 9 scored dimensions.
Claim: The report is objective, presenting attributed claims rather than subjective opinion.
“health officials fear” · exact text match
“Africa’s public health watchdog said” · exact text match
Why: The article attributes statements to officials and does not inject personal opinion.
Claim: The report is non-sensational, using measured language despite the seriousness.
“massive outbreak” · exact text match
“could be mutating” · exact text match
Why: Terms like 'massive' are descriptive but not hyperbolic; the tone remains factual.
Claim: The topic is inherently significant due to the scale of the outbreak and mutation concerns.
“massive outbreak” · exact text match
“cases have passed 4,000” · not found in supplied text
Why: The scale and novelty of the concern make it interesting.
Claim: The report describes the situation without prescribing actions.
“time for incremental action was over” · exact text match
Why: The statement is attributed to the watchdog, not the publisher, so it is descriptive reporting.
Claim: The report is factual and non-opinionated.
“health officials fear” · exact text match
“said the time for incremental action was over” · exact text match
Why: All statements are attributed, and no editorial opinion is offered.
Claim: The report is credible due to attribution and factual reporting.
“health officials fear” · exact text match
“Africa’s public health watchdog said” · exact text match
Why: Clear sourcing and no unsupported assertions.
Claim: The report takes a scientific approach to a medical issue.
“Ebola virus” · exact text match
“could be mutating” · exact text match
Why: The framing is empirical and disease-focused.
Claim: The report demonstrates honesty by clearly attributing sources.
“health officials fear” · exact text match
“Africa’s public health watchdog said” · exact text match
Why: Attribution is explicit, indicating transparency.
Claim: The report is truth-seeking, presenting official statements without distortion.
“could be mutating” · exact text match
“cases have passed 4,000” · not found in supplied text
Why: It relies on verifiable data and attributed concerns.
The article is extremely brief, limiting the depth of evidence for bias classification.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed. Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster. · 5 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday. At least 717 patients were in isolation while 749 patients have recovered.” · exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
Reporting on the Ebola outbreak uses urgent language and authoritative sources while including a prominent fundraising appeal.
The Bundibugyo virus responsible has no approved treatment or vaccine; the outbreak is the second-largest on record after the 2014-2016 West Africa outbreak.
Automated analysis; not human reviewed. Limitations: The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing. · 8 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 5 of 8 scored dimensions.
Claim: The article uses sensational language in the headline and quotes to heighten urgency.
“Over 1,700 dead from world's fastest-spreading Ebola outbreak as WHO offers dire warning” · exact text match
“The world’s fastest-growing Ebola outbreak is now spreading at a rate that outpaces efforts to contain it” · exact text match
Why: The headline and opening sentence use superlatives like 'fastest-spreading' and 'dire warning', which are sensational but supported by factual data.
Claim: The article emphasizes alarming spread and fatal outcomes to evoke fear.
“the outbreak is still "spreading at an alarming and unprecedented rate"” · not found in supplied text
“44 were fatal” · exact text match
Why: Direct quotes and statistics highlight rapid transmission and high fatality, framing the situation as urgent and fearful.
Claim: The article relies heavily on statements from WHO, Africa CDC, and Doctors Without Borders to establish credibility.
“WHO Director-General Tedros Adhanom Ghebreyesus stated” · exact text match
“Dr. Jean Kaseya, head of the Africa Centers for Disease Control, noted” · exact text match
Why: Multiple authoritative sources are quoted without countervailing voices, but this is appropriate for a health crisis where such authorities are the primary information sources.
Claim: The article evokes negative emotions by highlighting deaths and suffering.
“attributed the deaths of his two brothers from Ebola to the strike” · exact text match
“1,751 deaths” · exact text match
Why: Personal tragedy and high death toll create a negative emotional tone, but the reporting remains largely factual.
Claim: The article is highly credible due to clear attribution and data sourcing.
“according to the latest data from Congo’s Ministry of Health” · exact text match
“He told The Associated Press” · not found in supplied text
Why: Numbers are attributed to official sources, quotes are from named individuals and organizations, and the reporting is consistent with standard journalistic practice.
Claim: The article includes a prominent fundraising paragraph promoting donations to the publisher.
“Your donation allows us to keep sending journalists to speak to both sides of the story” · exact text match
“we choose not to lock Americans out of our reporting and analysis with paywalls” · exact text match
Why: A block of text explicitly asks for donations and promotes the publisher's values, which is a form of advertising for the publication itself.
Claim: The article provides detailed, informative data on the outbreak.
“77 most recent cases reported in 24 hours, 44 were fatal” · exact text match
“at least 60 to 70 percent of new cases emerging from individuals not being monitored” · exact text match
Why: Includes specific metrics like case numbers, fatality rate, contact tracing failure rate, and funding figures, indicating depth and intelligence.
The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
Neutral factual reporting on the Ebola outbreak and WHO response, with no evident framing bias beyond straightforward attribution and data presentation.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 0 of 3 scored dimensions.
Claim: The article presents facts without opinion.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: The sentence reports an event and cites a factual claim without evaluative language.
Claim: The article maintains a neutral emotional tone.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: No emotional language; factual reporting.
Claim: The article demonstrates high credibility through attribution and data.
“"according to the latest data from Congo’s Ministry of Health"” · not found in supplied text
“"Dr Jean Kaseya, Director-General of the Africa Centres for Disease Control, noted"” · not found in supplied text
Why: Multiple attributions to official sources and named experts enhance trustworthiness.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed. Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster. · 5 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday. At least 717 patients were in isolation while 749 patients have recovered.” · exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
August 04, 2026 · 0 shares
Reliance on official WHO statements and statistical data with a neutral factual tone.
Automated analysis; not human reviewed. Limitations: Input includes many promotional blurbs that could be mistaken for article content, but analysis focused on the main text. · 2 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 2 scored dimensions.
Claim: The article maintains an objective framing by relying on attributed statements and numerical data.
“The World Health Organization (WHO) on Tuesday called for greater support to tackle the Ebola outbreak in the Democratic Republic of Congo (DRC), warning that the response is still struggling to keep pace with the spread of the disease.” · exact text match
“The Country has recorded 3,802 confirmed Ebola cases, including 1,707 deaths.” · exact text match
Why: The publisher presents facts and quotes without subjective commentary or emotional language.
Claim: The article demonstrates high credibility by naming specific WHO spokespersons and providing precise figures.
“WHO spokesman Tarik Jasarevic told reporters in Geneva.” · exact text match
“The Country has recorded 3,802 confirmed Ebola cases, including 1,707 deaths.” · exact text match
Why: The sources are identified and the data is specific, enhancing trustworthiness.
Input includes many promotional blurbs that could be mistaken for article content, but analysis focused on the main text.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed. Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster. · 5 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday. At least 717 patients were in isolation while 749 patients have recovered.” · exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
Reporting on the Ebola outbreak uses urgent language and authoritative sources while including a prominent fundraising appeal.
The Bundibugyo virus responsible has no approved treatment or vaccine; the outbreak is the second-largest on record after the 2014-2016 West Africa outbreak.
Automated analysis; not human reviewed. Limitations: The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing. · 8 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 5 of 8 scored dimensions.
Claim: The article uses sensational language in the headline and quotes to heighten urgency.
“Over 1,700 dead from world's fastest-spreading Ebola outbreak as WHO offers dire warning” · exact text match
“The world’s fastest-growing Ebola outbreak is now spreading at a rate that outpaces efforts to contain it” · exact text match
Why: The headline and opening sentence use superlatives like 'fastest-spreading' and 'dire warning', which are sensational but supported by factual data.
Claim: The article emphasizes alarming spread and fatal outcomes to evoke fear.
“the outbreak is still "spreading at an alarming and unprecedented rate"” · not found in supplied text
“44 were fatal” · exact text match
Why: Direct quotes and statistics highlight rapid transmission and high fatality, framing the situation as urgent and fearful.
Claim: The article relies heavily on statements from WHO, Africa CDC, and Doctors Without Borders to establish credibility.
“WHO Director-General Tedros Adhanom Ghebreyesus stated” · exact text match
“Dr. Jean Kaseya, head of the Africa Centers for Disease Control, noted” · exact text match
Why: Multiple authoritative sources are quoted without countervailing voices, but this is appropriate for a health crisis where such authorities are the primary information sources.
Claim: The article evokes negative emotions by highlighting deaths and suffering.
“attributed the deaths of his two brothers from Ebola to the strike” · exact text match
“1,751 deaths” · exact text match
Why: Personal tragedy and high death toll create a negative emotional tone, but the reporting remains largely factual.
Claim: The article is highly credible due to clear attribution and data sourcing.
“according to the latest data from Congo’s Ministry of Health” · exact text match
“He told The Associated Press” · not found in supplied text
Why: Numbers are attributed to official sources, quotes are from named individuals and organizations, and the reporting is consistent with standard journalistic practice.
Claim: The article includes a prominent fundraising paragraph promoting donations to the publisher.
“Your donation allows us to keep sending journalists to speak to both sides of the story” · exact text match
“we choose not to lock Americans out of our reporting and analysis with paywalls” · exact text match
Why: A block of text explicitly asks for donations and promotes the publisher's values, which is a form of advertising for the publication itself.
Claim: The article provides detailed, informative data on the outbreak.
“77 most recent cases reported in 24 hours, 44 were fatal” · exact text match
“at least 60 to 70 percent of new cases emerging from individuals not being monitored” · exact text match
Why: Includes specific metrics like case numbers, fatality rate, contact tracing failure rate, and funding figures, indicating depth and intelligence.
The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing.
August 04, 2026 · 0 shares
Straightforward reporting of a Chinese Foreign Ministry statement on Ebola support, with no editorial slant.
Automated analysis; not human reviewed. Limitations: The article is very short and contains only a government statement; limited independent information. · 1 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 1 scored dimensions.
Claim: The article covers a government statement, making it political in nature, but the reporting is neutral.
“Spokesperson Lin Jian made the remarks in response to a question on the third Chinese government's medical expert team arriving in Kinshasa, capital of the Democratic Republic of the Congo (DRC), on August 1.” · exact text match
Why: The article focuses on a foreign ministry spokesperson's statement about China's international support, which is inherently political content.
The article is very short and contains only a government statement; limited independent information.
DRC communities and frontline workers
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed. Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster. · 5 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday. At least 717 patients were in isolation while 749 patients have recovered.” · exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
Neutral factual reporting on the Ebola outbreak and WHO response, with no evident framing bias beyond straightforward attribution and data presentation.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 0 of 3 scored dimensions.
Claim: The article presents facts without opinion.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: The sentence reports an event and cites a factual claim without evaluative language.
Claim: The article maintains a neutral emotional tone.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: No emotional language; factual reporting.
Claim: The article demonstrates high credibility through attribution and data.
“"according to the latest data from Congo’s Ministry of Health"” · not found in supplied text
“"Dr Jean Kaseya, Director-General of the Africa Centres for Disease Control, noted"” · not found in supplied text
Why: Multiple attributions to official sources and named experts enhance trustworthiness.
August 03, 2026 · 0 shares
Frames the Ebola outbreak as exacerbating maternal mortality through fear and misinformation, relying on statistical and anecdotal evidence from UNFPA and local health workers.
Automated analysis; not human reviewed. Limitations: The article text includes AI authorship disclosure and partial framing, but the substantive reporting is sourced; limited context on the political and healthcare funding background. · 2 of 52 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 2 scored dimensions.
Claim: The article maintains a neutral, unemotional tone despite the serious subject.
“The outbreak has strained Congo’s healthcare system, with facilities in five affected provinces redirecting staff and supplies toward Ebola response, reducing maternal care access.” · exact text match
Why: The language is factual and restrained, lacking emotional modifiers.
Claim: The article cites multiple named sources and specific data, indicating high credibility.
“According to U.N. Population Fund (UNFPA) data, weekly maternal deaths in Ituri rose from an average of 3.1 before the outbreak to 5.8 between May 25 and July 19.” · exact text match
Why: Direct attribution to UNFPA and other named experts, with specific figures and timeframes.
The article text includes AI authorship disclosure and partial framing, but the substantive reporting is sourced; limited context on the political and healthcare funding background.
Helium Bias
Story Blindspots
August 06, 2026 · 0 shares
The report conveys urgency about the Ebola outbreak through official concerns about mutation and a planned major response escalation, while maintaining a factual, attributed tone.
Automated analysis; not human reviewed. Limitations: The article is extremely brief, limiting the depth of evidence for bias classification. · 9 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 7 of 9 scored dimensions.
Claim: The report is objective, presenting attributed claims rather than subjective opinion.
“health officials fear” · exact text match
“Africa’s public health watchdog said” · exact text match
Why: The article attributes statements to officials and does not inject personal opinion.
Claim: The report is non-sensational, using measured language despite the seriousness.
“massive outbreak” · exact text match
“could be mutating” · exact text match
Why: Terms like 'massive' are descriptive but not hyperbolic; the tone remains factual.
Claim: The topic is inherently significant due to the scale of the outbreak and mutation concerns.
“massive outbreak” · exact text match
“cases have passed 4,000” · not found in supplied text
Why: The scale and novelty of the concern make it interesting.
Claim: The report describes the situation without prescribing actions.
“time for incremental action was over” · exact text match
Why: The statement is attributed to the watchdog, not the publisher, so it is descriptive reporting.
Claim: The report is factual and non-opinionated.
“health officials fear” · exact text match
“said the time for incremental action was over” · exact text match
Why: All statements are attributed, and no editorial opinion is offered.
Claim: The report is credible due to attribution and factual reporting.
“health officials fear” · exact text match
“Africa’s public health watchdog said” · exact text match
Why: Clear sourcing and no unsupported assertions.
Claim: The report takes a scientific approach to a medical issue.
“Ebola virus” · exact text match
“could be mutating” · exact text match
Why: The framing is empirical and disease-focused.
Claim: The report demonstrates honesty by clearly attributing sources.
“health officials fear” · exact text match
“Africa’s public health watchdog said” · exact text match
Why: Attribution is explicit, indicating transparency.
Claim: The report is truth-seeking, presenting official statements without distortion.
“could be mutating” · exact text match
“cases have passed 4,000” · not found in supplied text
Why: It relies on verifiable data and attributed concerns.
The article is extremely brief, limiting the depth of evidence for bias classification.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed. Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster. · 5 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday. At least 717 patients were in isolation while 749 patients have recovered.” · exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
Reporting on the Ebola outbreak uses urgent language and authoritative sources while including a prominent fundraising appeal.
The Bundibugyo virus responsible has no approved treatment or vaccine; the outbreak is the second-largest on record after the 2014-2016 West Africa outbreak.
Automated analysis; not human reviewed. Limitations: The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing. · 8 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 5 of 8 scored dimensions.
Claim: The article uses sensational language in the headline and quotes to heighten urgency.
“Over 1,700 dead from world's fastest-spreading Ebola outbreak as WHO offers dire warning” · exact text match
“The world’s fastest-growing Ebola outbreak is now spreading at a rate that outpaces efforts to contain it” · exact text match
Why: The headline and opening sentence use superlatives like 'fastest-spreading' and 'dire warning', which are sensational but supported by factual data.
Claim: The article emphasizes alarming spread and fatal outcomes to evoke fear.
“the outbreak is still "spreading at an alarming and unprecedented rate"” · not found in supplied text
“44 were fatal” · exact text match
Why: Direct quotes and statistics highlight rapid transmission and high fatality, framing the situation as urgent and fearful.
Claim: The article relies heavily on statements from WHO, Africa CDC, and Doctors Without Borders to establish credibility.
“WHO Director-General Tedros Adhanom Ghebreyesus stated” · exact text match
“Dr. Jean Kaseya, head of the Africa Centers for Disease Control, noted” · exact text match
Why: Multiple authoritative sources are quoted without countervailing voices, but this is appropriate for a health crisis where such authorities are the primary information sources.
Claim: The article evokes negative emotions by highlighting deaths and suffering.
“attributed the deaths of his two brothers from Ebola to the strike” · exact text match
“1,751 deaths” · exact text match
Why: Personal tragedy and high death toll create a negative emotional tone, but the reporting remains largely factual.
Claim: The article is highly credible due to clear attribution and data sourcing.
“according to the latest data from Congo’s Ministry of Health” · exact text match
“He told The Associated Press” · not found in supplied text
Why: Numbers are attributed to official sources, quotes are from named individuals and organizations, and the reporting is consistent with standard journalistic practice.
Claim: The article includes a prominent fundraising paragraph promoting donations to the publisher.
“Your donation allows us to keep sending journalists to speak to both sides of the story” · exact text match
“we choose not to lock Americans out of our reporting and analysis with paywalls” · exact text match
Why: A block of text explicitly asks for donations and promotes the publisher's values, which is a form of advertising for the publication itself.
Claim: The article provides detailed, informative data on the outbreak.
“77 most recent cases reported in 24 hours, 44 were fatal” · exact text match
“at least 60 to 70 percent of new cases emerging from individuals not being monitored” · exact text match
Why: Includes specific metrics like case numbers, fatality rate, contact tracing failure rate, and funding figures, indicating depth and intelligence.
The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed. Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster. · 5 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday. At least 717 patients were in isolation while 749 patients have recovered.” · exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
Reporting on the Ebola outbreak uses urgent language and authoritative sources while including a prominent fundraising appeal.
The Bundibugyo virus responsible has no approved treatment or vaccine; the outbreak is the second-largest on record after the 2014-2016 West Africa outbreak.
Automated analysis; not human reviewed. Limitations: The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing. · 8 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 5 of 8 scored dimensions.
Claim: The article uses sensational language in the headline and quotes to heighten urgency.
“Over 1,700 dead from world's fastest-spreading Ebola outbreak as WHO offers dire warning” · exact text match
“The world’s fastest-growing Ebola outbreak is now spreading at a rate that outpaces efforts to contain it” · exact text match
Why: The headline and opening sentence use superlatives like 'fastest-spreading' and 'dire warning', which are sensational but supported by factual data.
Claim: The article emphasizes alarming spread and fatal outcomes to evoke fear.
“the outbreak is still "spreading at an alarming and unprecedented rate"” · not found in supplied text
“44 were fatal” · exact text match
Why: Direct quotes and statistics highlight rapid transmission and high fatality, framing the situation as urgent and fearful.
Claim: The article relies heavily on statements from WHO, Africa CDC, and Doctors Without Borders to establish credibility.
“WHO Director-General Tedros Adhanom Ghebreyesus stated” · exact text match
“Dr. Jean Kaseya, head of the Africa Centers for Disease Control, noted” · exact text match
Why: Multiple authoritative sources are quoted without countervailing voices, but this is appropriate for a health crisis where such authorities are the primary information sources.
Claim: The article evokes negative emotions by highlighting deaths and suffering.
“attributed the deaths of his two brothers from Ebola to the strike” · exact text match
“1,751 deaths” · exact text match
Why: Personal tragedy and high death toll create a negative emotional tone, but the reporting remains largely factual.
Claim: The article is highly credible due to clear attribution and data sourcing.
“according to the latest data from Congo’s Ministry of Health” · exact text match
“He told The Associated Press” · not found in supplied text
Why: Numbers are attributed to official sources, quotes are from named individuals and organizations, and the reporting is consistent with standard journalistic practice.
Claim: The article includes a prominent fundraising paragraph promoting donations to the publisher.
“Your donation allows us to keep sending journalists to speak to both sides of the story” · exact text match
“we choose not to lock Americans out of our reporting and analysis with paywalls” · exact text match
Why: A block of text explicitly asks for donations and promotes the publisher's values, which is a form of advertising for the publication itself.
Claim: The article provides detailed, informative data on the outbreak.
“77 most recent cases reported in 24 hours, 44 were fatal” · exact text match
“at least 60 to 70 percent of new cases emerging from individuals not being monitored” · exact text match
Why: Includes specific metrics like case numbers, fatality rate, contact tracing failure rate, and funding figures, indicating depth and intelligence.
The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
Neutral factual reporting on the Ebola outbreak and WHO response, with no evident framing bias beyond straightforward attribution and data presentation.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 0 of 3 scored dimensions.
Claim: The article presents facts without opinion.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: The sentence reports an event and cites a factual claim without evaluative language.
Claim: The article maintains a neutral emotional tone.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: No emotional language; factual reporting.
Claim: The article demonstrates high credibility through attribution and data.
“"according to the latest data from Congo’s Ministry of Health"” · not found in supplied text
“"Dr Jean Kaseya, Director-General of the Africa Centres for Disease Control, noted"” · not found in supplied text
Why: Multiple attributions to official sources and named experts enhance trustworthiness.
Neutral factual reporting on the Ebola outbreak and WHO response, with no evident framing bias beyond straightforward attribution and data presentation.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 0 of 3 scored dimensions.
Claim: The article presents facts without opinion.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: The sentence reports an event and cites a factual claim without evaluative language.
Claim: The article maintains a neutral emotional tone.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: No emotional language; factual reporting.
Claim: The article demonstrates high credibility through attribution and data.
“"according to the latest data from Congo’s Ministry of Health"” · not found in supplied text
“"Dr Jean Kaseya, Director-General of the Africa Centres for Disease Control, noted"” · not found in supplied text
Why: Multiple attributions to official sources and named experts enhance trustworthiness.
August 03, 2026 · 0 shares
Employs a Marxist anti-imperialist framing that attributes the outbreak's severity to capitalist and imperialist systems and prescribes working-class revolution and public ownership of health infrastructure.
Automated analysis; not human reviewed. · 17 of 52 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 11 of 17 scored dimensions.
Claim: The article frames the outbreak severity and response failure as consequences of capitalism, imperialism, and private market priorities.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands and place them under its own democratic control, so that what gets developed answers to human need rather than to shareholder return and threat designation.” · exact text match
“Such actions define a calculated and psychopathic social murder: the foreseeable, documented and accepted killing of a population whose lives were weighed against procurement priorities and found to be worth less.” · exact text match
Why: These exact quotes explicitly attribute the lack of vaccines and inadequate response to capitalist/imperialist structures and call for working-class control, strongly indicating a far-left, anti-capitalist stance.
Claim: The article interjects strong moral judgments and subjective interpretations into what is otherwise a factual epidemiological report.
“That is not a failure of capacity. It is a decision, and its result will be counted in the dead.” · exact text match
Why: The quote asserts that the outcome is a conscious decision and attaches moral weight to it, which is subjective framing beyond the reported data.
Claim: The article uses extreme, emotionally charged language to describe the response and its consequences.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: The phrase 'calculated and psychopathic social murder' is sensational, exceeding objective reporting and intended to provoke strong emotional reaction.
Claim: The article repeatedly prescribes specific political and economic actions as necessary solutions.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands and place them under its own democratic control.” · not found in supplied text
Why: The use of 'must' and the imperative prescription of a political program clearly show a prescriptive rather than descriptive stance.
Claim: The article criticizes military spending and advocates for reallocation to health, indicating a dovish stance.
“The United States found $87.6 billion for a military supplemental in a week but could not provide the mere $115 million for the WHO’s budget.” · exact text match
Why: This contrast criticizes military expenditures and implies a preference against hawkish priorities, but the dimension is not strongly developed.
Claim: The article emphasizes the worst-case projections and the response being outpaced, inducing fear.
“the outbreak continued to outpace the response” · exact text match
“worst-case scenario” · exact text match
Why: Combining 'outpaced' and 'worst-case scenario' amplifies the sense of danger and urgency, though it is fact-based.
Claim: The article is heavily opinionated, with explicit political analysis and calls to action.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: The strong moral condemnation is clearly opinion, not neutral fact-reporting.
Claim: The article is explicitly political, calling for a unified political struggle against imperialism.
“This requires a unified political struggle by workers in Africa, Europe and the Americas against the imperialist order that has organized global medicine around its own security, and the building of sections of the International Committee of the Fourth International.” · exact text match
Why: The direct call for a political struggle and reference to a specific political organization makes the article overtly political.
Claim: The article portrays the Congolese population and health workers as victims of systemic neglect.
“While Congolese doctors have been treating Ebola patients for two months without pay, Western governments flew their own nationals to hospitals in Frankfurt and Berlin.” · exact text match
Why: The contrast highlights victimization, but it is a factual comparison; the framing is only moderately victim-focused.
Claim: The article presents a coherent ideological framework (Marxist anti-imperialism) and applies it consistently.
“the imperialist order that has organized global medicine around its own security” · exact text match
Why: The phrase 'imperialist order' signals a consistent ideological lens applied to interpret the events.
Claim: The article is deeply critical of existing political, economic, and health institutions, framing them as complicit in preventable deaths.
“That is not a failure of capacity. It is a decision, and its result will be counted in the dead.” · exact text match
Why: The quote blames the outcome on a decision attributed to the institutional/systemic establishment, showing strong anti-establishment framing.
Claim: The article conveys strong negative emotions, particularly anger and condemnation.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: The language is morally charged and anger-inducing, indicating a negative emotional tone.
Claim: The article points out a double standard in treatment of Western nationals versus Congolese.
“While Congolese doctors have been treating Ebola patients for two months without pay, Western governments flew their own nationals to hospitals in Frankfurt and Berlin.” · exact text match
Why: The direct juxtaposition highlights an unequal application of resources and care, a clear double standard.
Claim: The article is strongly anti-corporate, criticizing pharmaceutical and biotechnology industries.
“answers to human need rather than to shareholder return” · exact text match
Why: The contrast between human need and shareholder return is explicitly anti-corporate.
Claim: The article advocates for collective ownership and democratic control, rejecting individualistic market solutions.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands and place them under its own democratic control.” · not found in supplied text
Why: The promotion of collective ownership and democratic control reflects a strong collectivist orientation.
Claim: The article uses emotionally manipulative language and selective framing to induce outrage.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: While the language is strong, it is based on factual underpinnings; the manipulation is moderate, as the core facts are not fabricated.
Claim: The article explicitly advocates Marxist class-based analysis and revolutionary action.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands” · exact text match
“the building of sections of the International Committee of the Fourth International” · exact text match
Why: These quotes directly invoke the working class, call for expropriation of private industry, and cite a Trotskyist international, unmistakably Marxist.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed. Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster. · 5 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday. At least 717 patients were in isolation while 749 patients have recovered.” · exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed. Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster. · 5 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday. At least 717 patients were in isolation while 749 patients have recovered.” · exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
Neutral factual reporting on the Ebola outbreak and WHO response, with no evident framing bias beyond straightforward attribution and data presentation.
Automated analysis; not human reviewed. · 3 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 0 of 3 scored dimensions.
Claim: The article presents facts without opinion.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: The sentence reports an event and cites a factual claim without evaluative language.
Claim: The article maintains a neutral emotional tone.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: No emotional language; factual reporting.
Claim: The article demonstrates high credibility through attribution and data.
“"according to the latest data from Congo’s Ministry of Health"” · not found in supplied text
“"Dr Jean Kaseya, Director-General of the Africa Centres for Disease Control, noted"” · not found in supplied text
Why: Multiple attributions to official sources and named experts enhance trustworthiness.
August 04, 2026 · 0 shares
Reliance on official WHO statements and statistical data with a neutral factual tone.
Automated analysis; not human reviewed. Limitations: Input includes many promotional blurbs that could be mistaken for article content, but analysis focused on the main text. · 2 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 2 scored dimensions.
Claim: The article maintains an objective framing by relying on attributed statements and numerical data.
“The World Health Organization (WHO) on Tuesday called for greater support to tackle the Ebola outbreak in the Democratic Republic of Congo (DRC), warning that the response is still struggling to keep pace with the spread of the disease.” · exact text match
“The Country has recorded 3,802 confirmed Ebola cases, including 1,707 deaths.” · exact text match
Why: The publisher presents facts and quotes without subjective commentary or emotional language.
Claim: The article demonstrates high credibility by naming specific WHO spokespersons and providing precise figures.
“WHO spokesman Tarik Jasarevic told reporters in Geneva.” · exact text match
“The Country has recorded 3,802 confirmed Ebola cases, including 1,707 deaths.” · exact text match
Why: The sources are identified and the data is specific, enhancing trustworthiness.
Input includes many promotional blurbs that could be mistaken for article content, but analysis focused on the main text.
August 06, 2026 · 0 shares
The report conveys urgency about the Ebola outbreak through official concerns about mutation and a planned major response escalation, while maintaining a factual, attributed tone.
Automated analysis; not human reviewed. Limitations: The article is extremely brief, limiting the depth of evidence for bias classification. · 9 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 7 of 9 scored dimensions.
Claim: The report is objective, presenting attributed claims rather than subjective opinion.
“health officials fear” · exact text match
“Africa’s public health watchdog said” · exact text match
Why: The article attributes statements to officials and does not inject personal opinion.
Claim: The report is non-sensational, using measured language despite the seriousness.
“massive outbreak” · exact text match
“could be mutating” · exact text match
Why: Terms like 'massive' are descriptive but not hyperbolic; the tone remains factual.
Claim: The topic is inherently significant due to the scale of the outbreak and mutation concerns.
“massive outbreak” · exact text match
“cases have passed 4,000” · not found in supplied text
Why: The scale and novelty of the concern make it interesting.
Claim: The report describes the situation without prescribing actions.
“time for incremental action was over” · exact text match
Why: The statement is attributed to the watchdog, not the publisher, so it is descriptive reporting.
Claim: The report is factual and non-opinionated.
“health officials fear” · exact text match
“said the time for incremental action was over” · exact text match
Why: All statements are attributed, and no editorial opinion is offered.
Claim: The report is credible due to attribution and factual reporting.
“health officials fear” · exact text match
“Africa’s public health watchdog said” · exact text match
Why: Clear sourcing and no unsupported assertions.
Claim: The report takes a scientific approach to a medical issue.
“Ebola virus” · exact text match
“could be mutating” · exact text match
Why: The framing is empirical and disease-focused.
Claim: The report demonstrates honesty by clearly attributing sources.
“health officials fear” · exact text match
“Africa’s public health watchdog said” · exact text match
Why: Attribution is explicit, indicating transparency.
Claim: The report is truth-seeking, presenting official statements without distortion.
“could be mutating” · exact text match
“cases have passed 4,000” · not found in supplied text
Why: It relies on verifiable data and attributed concerns.
The article is extremely brief, limiting the depth of evidence for bias classification.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed. Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster. · 5 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday. At least 717 patients were in isolation while 749 patients have recovered.” · exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
Reporting on the Ebola outbreak uses urgent language and authoritative sources while including a prominent fundraising appeal.
The Bundibugyo virus responsible has no approved treatment or vaccine; the outbreak is the second-largest on record after the 2014-2016 West Africa outbreak.
Automated analysis; not human reviewed. Limitations: The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing. · 8 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 5 of 8 scored dimensions.
Claim: The article uses sensational language in the headline and quotes to heighten urgency.
“Over 1,700 dead from world's fastest-spreading Ebola outbreak as WHO offers dire warning” · exact text match
“The world’s fastest-growing Ebola outbreak is now spreading at a rate that outpaces efforts to contain it” · exact text match
Why: The headline and opening sentence use superlatives like 'fastest-spreading' and 'dire warning', which are sensational but supported by factual data.
Claim: The article emphasizes alarming spread and fatal outcomes to evoke fear.
“the outbreak is still "spreading at an alarming and unprecedented rate"” · not found in supplied text
“44 were fatal” · exact text match
Why: Direct quotes and statistics highlight rapid transmission and high fatality, framing the situation as urgent and fearful.
Claim: The article relies heavily on statements from WHO, Africa CDC, and Doctors Without Borders to establish credibility.
“WHO Director-General Tedros Adhanom Ghebreyesus stated” · exact text match
“Dr. Jean Kaseya, head of the Africa Centers for Disease Control, noted” · exact text match
Why: Multiple authoritative sources are quoted without countervailing voices, but this is appropriate for a health crisis where such authorities are the primary information sources.
Claim: The article evokes negative emotions by highlighting deaths and suffering.
“attributed the deaths of his two brothers from Ebola to the strike” · exact text match
“1,751 deaths” · exact text match
Why: Personal tragedy and high death toll create a negative emotional tone, but the reporting remains largely factual.
Claim: The article is highly credible due to clear attribution and data sourcing.
“according to the latest data from Congo’s Ministry of Health” · exact text match
“He told The Associated Press” · not found in supplied text
Why: Numbers are attributed to official sources, quotes are from named individuals and organizations, and the reporting is consistent with standard journalistic practice.
Claim: The article includes a prominent fundraising paragraph promoting donations to the publisher.
“Your donation allows us to keep sending journalists to speak to both sides of the story” · exact text match
“we choose not to lock Americans out of our reporting and analysis with paywalls” · exact text match
Why: A block of text explicitly asks for donations and promotes the publisher's values, which is a form of advertising for the publication itself.
Claim: The article provides detailed, informative data on the outbreak.
“77 most recent cases reported in 24 hours, 44 were fatal” · exact text match
“at least 60 to 70 percent of new cases emerging from individuals not being monitored” · exact text match
Why: Includes specific metrics like case numbers, fatality rate, contact tracing failure rate, and funding figures, indicating depth and intelligence.
The article text includes a lengthy fundraising appeal that may influence advertising and virtue signal bias assessments; the analysis treats it as part of the publisher framing.
August 04, 2026 · 0 shares
Straightforward reporting of a Chinese Foreign Ministry statement on Ebola support, with no editorial slant.
Automated analysis; not human reviewed. Limitations: The article is very short and contains only a government statement; limited independent information. · 1 of 53 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 1 of 1 scored dimensions.
Claim: The article covers a government statement, making it political in nature, but the reporting is neutral.
“Spokesperson Lin Jian made the remarks in response to a question on the third Chinese government's medical expert team arriving in Kinshasa, capital of the Democratic Republic of the Congo (DRC), on August 1.” · exact text match
Why: The article focuses on a foreign ministry spokesperson's statement about China's international support, which is inherently political content.
The article is very short and contains only a government statement; limited independent information.
August 03, 2026 · 0 shares
Frames the Ebola outbreak as exacerbating maternal mortality through fear and misinformation, relying on statistical and anecdotal evidence from UNFPA and local health workers.
Automated analysis; not human reviewed. Limitations: The article text includes AI authorship disclosure and partial framing, but the substantive reporting is sourced; limited context on the political and healthcare funding background. · 2 of 52 available dimensions scored; omitted dimensions are not treated as neutral. · Verified supporting quotes for 2 of 2 scored dimensions.
Claim: The article maintains a neutral, unemotional tone despite the serious subject.
“The outbreak has strained Congo’s healthcare system, with facilities in five affected provinces redirecting staff and supplies toward Ebola response, reducing maternal care access.” · exact text match
Why: The language is factual and restrained, lacking emotional modifiers.
Claim: The article cites multiple named sources and specific data, indicating high credibility.
“According to U.N. Population Fund (UNFPA) data, weekly maternal deaths in Ituri rose from an average of 3.1 before the outbreak to 5.8 between May 25 and July 19.” · exact text match
Why: Direct attribution to UNFPA and other named experts, with specific figures and timeframes.
The article text includes AI authorship disclosure and partial framing, but the substantive reporting is sourced; limited context on the political and healthcare funding background.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
August 06, 2026 · 0 shares
Neutral news reporting on the Ebola outbreak, relying on official sources and specific data, without editorial slant.
Automated analysis; not human reviewed.
Limitations: No significant input limitations; article is straightforward news from a reputable public broadcaster.
·
5 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 1 of 5 scored dimensions.
Claim: The article covers a significant global health emergency with multiple facets.
“WHO's Tedros warned that 'we must urgently and massively scale up all our efforts'” · not found in supplied text
“The 17th Ebola outbreak in DRC's history is already the fastest-spreading and the second-most deadly outbreak on record.” · exact text match
“US State Department pledged another $242 million” · exact text match
Why: Subject matter is inherently significant, but article is straightforward.
Claim: The article maintains a neutral emotional tone.
“3,874 cases, including 1,751 deaths, as of Monday.
At least 717 patients were in isolation while 749 patients have recovered.”
· exact text match
Why: Uses dry numbers; no emotional adjectives.
Claim: The article uses multiple named institutional sources and on-the-ground reporting.
“DW correspondent Wendy Bashi reported...” · not found in supplied text
“According to the most recent data from Congo's Ministry of Health...” · not found in supplied text
“WHO's Tedros said...” · not found in supplied text
Why: Diverse, attributed sources enhance credibility.
Claim: The article maintains high integrity by including multiple perspectives and acknowledging challenges.
“Medical charity Doctors Without Borders warned on Wednesday that the rare strain was still 'spreading at an alarming and unprecedented rate' in a remote area of DRC with poor infrastructure.” · not found in supplied text
“Dr. Jean Kaseya, the head of the Africa Centers for Disease and Control, warned that 'contact tracing is not working' and more and more cases were detected late, reducing the chances of survival.” · not found in supplied text
Why: Includes critical voices from MSF and Africa CDC, not only WHO.
Claim: The article provides comprehensive, multi-sourced information with nuanced detail.
“It had confirmed 3,874 cases, including 1,751 deaths...” · not found in supplied text
“The response is expanding but is still not reaching communities quickly enough to break transmission chains, the group said.” · not found in supplied text
“Reports of many front line health workers going on strike, either in disputes over pay levels or non-payment, or a mixture of the two, have only worsened already inadequate access to healthcare.” · exact text match
Why: Covers numbers, challenges, multiple actors, local context.
No significant input limitations; article is straightforward news from a reputable public broadcaster.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
Neutral factual reporting on the Ebola outbreak and WHO response, with no evident framing bias beyond straightforward attribution and data presentation.
Automated analysis; not human reviewed.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 0 of 3 scored dimensions.
Claim: The article presents facts without opinion.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: The sentence reports an event and cites a factual claim without evaluative language.
Claim: The article maintains a neutral emotional tone.
“"The head of the World Health Organisation (WHO) has arrived in Congo to bolster efforts against the world’s fastest-growing Ebola outbreak"” · not found in supplied text
Why: No emotional language; factual reporting.
Claim: The article demonstrates high credibility through attribution and data.
“"according to the latest data from Congo’s Ministry of Health"” · not found in supplied text
“"Dr Jean Kaseya, Director-General of the Africa Centres for Disease Control, noted"” · not found in supplied text
Why: Multiple attributions to official sources and named experts enhance trustworthiness.
August 05, 2026 · 0 shares
Uses urgent language ('pleads', 'raging') to frame the Ebola outbreak as a growing crisis requiring immediate support.
Automated analysis; not human reviewed.
Limitations: Article text is truncated and includes subscription prompts; analysis based on the first few sentences.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 3 of 3 scored dimensions.
Claim: The article presents factual claims with attribution, showing an objective stance.
“The outbreak is the biggest ever to have hit the Democratic Republic of Congo” · exact text match
Why: The claim is stated as a fact and attributed to the WHO, with no opinion or subjective language in the main body.
Claim: The article uses emotionally charged words like 'pleads' and 'raging', indicating a negative emotional tone.
“WHO pleads for more support” · exact text match
“outbreak raging in Congo” · exact text match
Why: The headline uses 'pleads' (urgent, desperate) and the body describes the outbreak as 'raging', both of which evoke a negative emotional response.
Claim: The article attributes information to a named, credible source with location, enhancing credibility.
“WHO spokesman Tarik Jasarevic told reporters in Geneva” · exact text match
Why: Direct attribution to a specific official and location provides verifiable sourcing, indicating high credibility within the text.
Article text is truncated and includes subscription prompts; analysis based on the first few sentences.
August 04, 2026 · 0 shares
Reliance on official WHO statements and statistical data with a neutral factual tone.
Automated analysis; not human reviewed.
Limitations: Input includes many promotional blurbs that could be mistaken for article content, but analysis focused on the main text.
·
2 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 2 scored dimensions.
Claim: The article maintains an objective framing by relying on attributed statements and numerical data.
“The World Health Organization (WHO) on Tuesday called for greater support to tackle the Ebola outbreak in the Democratic Republic of Congo (DRC), warning that the response is still struggling to keep pace with the spread of the disease.” · exact text match
“The Country has recorded 3,802 confirmed Ebola cases, including 1,707 deaths.” · exact text match
Why: The publisher presents facts and quotes without subjective commentary or emotional language.
Claim: The article demonstrates high credibility by naming specific WHO spokespersons and providing precise figures.
“WHO spokesman Tarik Jasarevic told reporters in Geneva.” · exact text match
“The Country has recorded 3,802 confirmed Ebola cases, including 1,707 deaths.” · exact text match
Why: The sources are identified and the data is specific, enhancing trustworthiness.
Input includes many promotional blurbs that could be mistaken for article content, but analysis focused on the main text.
August 06, 2026 · 0 shares
Frames the outbreak as alarmingly fast-spreading due to systemic failures and conflict, relying on official health sources without advocacy.
Automated analysis; not human reviewed.
·
4 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 4 scored dimensions.
Claim: The article is highly objective, relying on official statements and data without editorializing.
“Health officials say the current epidemic is spreading five times faster than previous outbreaks did at this stage.” · exact text match
“WHO recorded more than 28,000 cases and 11,000 deaths.” · not found in supplied text
Why: The article attributes key claims to health officials and WHO, uses factual language, and avoids opinion or commentary.
Claim: The article is descriptive, explaining causes without prescribing solutions.
“Delayed detection, overwhelmed surveillance, military conflict and a lack of vaccines and treatments for the species of the virus involved have allowed the disease to outrun containment efforts this time.” · exact text match
Why: Lists causal factors but does not advocate for any specific policy or action.
Claim: The article appears credible due to attribution and specific data.
“WHO recorded more than 28,000 cases and 11,000 deaths.” · not found in supplied text
“Health officials say the current epidemic is spreading five times faster than previous outbreaks did at this stage.” · exact text match
Why: Internal consistency, specific numbers, and clear sourcing support credibility, though full verification is not possible.
Claim: The article presents a rational causal explanation based on identified factors.
“Delayed detection, overwhelmed surveillance, military conflict and a lack of vaccines and treatments for the species of the virus involved have allowed the disease to outrun containment efforts this time.” · exact text match
Why: Provides a logical chain of causes, no emotional or irrational appeals.
August 03, 2026 · 0 shares
Frames the Ebola outbreak as exacerbating maternal mortality through fear and misinformation, relying on statistical and anecdotal evidence from UNFPA and local health workers.
Automated analysis; not human reviewed.
Limitations: The article text includes AI authorship disclosure and partial framing, but the substantive reporting is sourced; limited context on the political and healthcare funding background.
·
2 of 52 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 2 scored dimensions.
Claim: The article maintains a neutral, unemotional tone despite the serious subject.
“The outbreak has strained Congo’s healthcare system, with facilities in five affected provinces redirecting staff and supplies toward Ebola response, reducing maternal care access.” · exact text match
Why: The language is factual and restrained, lacking emotional modifiers.
Claim: The article cites multiple named sources and specific data, indicating high credibility.
“According to U.N. Population Fund (UNFPA) data, weekly maternal deaths in Ituri rose from an average of 3.1 before the outbreak to 5.8 between May 25 and July 19.” · exact text match
Why: Direct attribution to UNFPA and other named experts, with specific figures and timeframes.
The article text includes AI authorship disclosure and partial framing, but the substantive reporting is sourced; limited context on the political and healthcare funding background.
August 04, 2026 · 0 shares
Factual reporting on the Ebola outbreak provides data and official sources without editorializing, emphasizing the severity and response challenges.
Automated analysis; not human reviewed.
·
19 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 13 of 19 scored dimensions.
Claim: The article is highly objective, relying on verifiable data and attributed quotes rather than subjective opinion.
“As of Tuesday, 3,802 cases had been recorded, with 1,707 deaths, the latest government update showed.” · exact text match
“Contact tracing is not working, said Kaseya, we don’t like the trajectory of this outbreak” · not found in supplied text
Why: The text is dominated by numbers and direct quotes from officials, with no editorial commentary.
Claim: The article avoids sensational language and focuses on factual reporting.
“Ebola has killed more than 1,700 people in eastern Congo in what has become the fastest-growing outbreak of the disease” · exact text match
“It was not clear when the outbreak will reach its peak” · exact text match
Why: Even when describing severity, the phrasing is measured and attributed to data.
Claim: The article covers a newsworthy and significant public health event.
“the fastest-growing outbreak of the disease” · exact text match
“the second largest outbreak (ever) in the world” · exact text match
Why: The content is inherently interesting due to scale and urgency.
Claim: The article describes the situation without prescribing actions or advocating for specific policies.
“Two clinical trials for post-exposure prophylaxis drugs are ongoing in Ituri province as well as two separate vaccine trials in the United Kingdom and Canada.” · exact text match
“A key challenge is that patient zero has yet to be identified” · exact text match
Why: The text reports on trials and challenges without telling readers what should be done.
Claim: The article is factual and avoids opinionated language.
“Ebola has killed more than 1,700 people in eastern Congo in what has become the fastest-growing outbreak of the disease, according to data” · exact text match
“It was not clear when the outbreak will reach its peak, Africa CDC director-general says” · exact text match
Why: All claims are attributed or supported by data.
Claim: The article is non-political and focuses on public health.
“Delays in contact tracing, difficulties accessing affected areas, mistrust from communities, and violence by armed groups and some residents have hampered the response” · exact text match
“The response is also hampered by a funding gap, attacks on health centers, an ongoing conflict in eastern Congo and mistrust among local communities.” · exact text match
Why: Mention of conflict is contextual and not used to assign blame or promote a political agenda.
Claim: The article does not oversimplify; it mentions multiple complicating factors.
“Delays in contact tracing, difficulties accessing affected areas, mistrust from communities, and violence by armed groups and some residents have hampered the response” · exact text match
“A key challenge is that patient zero has yet to be identified in the outbreak while displacement from armed conflict and illegal mining in the region have made it difficult to trace thousands” · exact text match
Why: Several distinct challenges are listed, showing complexity.
Claim: The article quotes health officials but also presents data, making moderate use of authority.
“Africa CDC Director-General Jean Kaseya said ... Contact tracing is not working” · not found in supplied text
“The World Health Organization said Tuesday that it was monitoring over 17,000 potential contacts” · exact text match
Why: Officials are cited for their expertise, which is standard in health reporting; not excessive.
Claim: The article avoids overconfidence by including expressions of uncertainty.
“It was not clear when the outbreak will reach its peak, Africa CDC director-general says” · exact text match
Why: Directly states uncertainty about the peak.
Claim: The main article contains no spam or promotional content.
“BUNIA, Congo — Ebola has killed more than 1,700 people in eastern Congo in what has become the fastest-growing outbreak of the disease” · exact text match
Why: No advertising or fluff in the substantive reporting.
Claim: The article maintains a neutral emotional tone, neither positive nor negative.
“Ebola has killed more than 1,700 people” · exact text match
“Contact tracing is not working, said Kaseya” · not found in supplied text
Why: Language is factual and restrained, without emotional adjectives.
Claim: The article shows strong credibility through clear attribution, specific data, and named officials.
“As of Tuesday, 3,802 cases had been recorded, with 1,707 deaths, the latest government update showed.” · exact text match
“Africa CDC Director-General Jean Kaseya said ...” · not found in supplied text
“The World Health Organization said Tuesday that it was monitoring over 17,000 potential contacts” · exact text match
Why: Sources are named and numbers are time-stamped; uncertainty is acknowledged.
Claim: The article presents information rationally using data and official statements.
“It was not clear when the outbreak will reach its peak, Africa CDC director-general says” · exact text match
“As of Tuesday, 3,802 cases had been recorded, with 1,707 deaths, the latest government update showed.” · exact text match
Why: The article acknowledges uncertainty and provides specific figures and attributions.
Claim: The article adheres to scientific and empirical reasoning.
“Two clinical trials for post-exposure prophylaxis drugs are ongoing ... two separate vaccine trials in the United Kingdom and Canada.” · not found in supplied text
“Enrollment in a highly anticipated study of two possible Ebola treatments recently started in Ituri.” · exact text match
Why: Focuses on medical research and data, no supernatural or superstitious elements.
Claim: The article exhibits human writing patterns, not AI-generated text.
“The director-general of the World Health Organization, Tedros Adhanom Ghebreyesus, was expected to arrive in the Congolese capital, Kinshasa, later on Tuesday and would visit Bunia later this week.” · exact text match
Why: Narrative flow and details about visits suggest human reporting.
Claim: The article demonstrates honesty by reporting challenges and including uncertainty.
“Contact tracing is not working, said Kaseya” · not found in supplied text
“It was not clear when the outbreak will reach its peak” · exact text match
Why: The article does not hide difficulties and correctly attributes statements.
Claim: The article is well-structured, informative, and provides relevant context.
“Two clinical trials for post-exposure prophylaxis drugs are ongoing in Ituri province as well as two separate vaccine trials in the United Kingdom and Canada.” · exact text match
“The latest outbreak has killed people at a quicker rate than any previous outbreak, including in 2014-2016 when 28,000 cases were reported” · exact text match
Why: Includes comparative data and ongoing research details.
Claim: The article is truth-seeking and evidence-based.
“It was not clear when the outbreak will reach its peak” · exact text match
“Contact tracing is not working” · exact text match
Why: Honestly reports failures and uncertainties.
August 06, 2026 · 0 shares
An attributed, data-driven account of the DRC Ebola outbreak focuses on WHO warnings and response challenges without editorializing or sensational framing.
Automated analysis; not human reviewed.
·
3 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 2 of 3 scored dimensions.
Claim: The report is objective.
“The World Health Organization (WHO) has warned that the Democratic Republic of Congo's Ebola outbreak is spreading faster than response efforts can contain it” · exact text match
Why: The statement is factual and attributed, with no subjective or opinionated language.
Claim: The report is not sensational.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
Why: The language is neutral and statistical, avoiding alarmist or exaggerated terms.
Claim: The report is highly credible due to sourcing and attribution.
“The outbreak has infected 3,874 people and killed 1,751, according to DR Congo's Ministry of Health” · exact text match
“Doctors Without Borders (MSF) warned on Wednesday that the outbreak is "spreading at an alarming and unprecedented rate," despite the expansion of response efforts.” · not found in supplied text
Why: The article attributes claims to named officials and organizations, provides statistics, and includes direct quotes.
August 04, 2026 · 0 shares
Straightforward reporting of a Chinese Foreign Ministry statement on Ebola support, with no editorial slant.
Automated analysis; not human reviewed.
Limitations: The article is very short and contains only a government statement; limited independent information.
·
1 of 53 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 1 of 1 scored dimensions.
Claim: The article covers a government statement, making it political in nature, but the reporting is neutral.
“Spokesperson Lin Jian made the remarks in response to a question on the third Chinese government's medical expert team arriving in Kinshasa, capital of the Democratic Republic of the Congo (DRC), on August 1.” · exact text match
Why: The article focuses on a foreign ministry spokesperson's statement about China's international support, which is inherently political content.
The article is very short and contains only a government statement; limited independent information.
August 03, 2026 · 0 shares
Employs a Marxist anti-imperialist framing that attributes the outbreak's severity to capitalist and imperialist systems and prescribes working-class revolution and public ownership of health infrastructure.
Automated analysis; not human reviewed.
·
17 of 52 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 11 of 17 scored dimensions.
Claim: The article frames the outbreak severity and response failure as consequences of capitalism, imperialism, and private market priorities.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands and place them under its own democratic control, so that what gets developed answers to human need rather than to shareholder return and threat designation.” · exact text match
“Such actions define a calculated and psychopathic social murder: the foreseeable, documented and accepted killing of a population whose lives were weighed against procurement priorities and found to be worth less.” · exact text match
Why: These exact quotes explicitly attribute the lack of vaccines and inadequate response to capitalist/imperialist structures and call for working-class control, strongly indicating a far-left, anti-capitalist stance.
Claim: The article interjects strong moral judgments and subjective interpretations into what is otherwise a factual epidemiological report.
“That is not a failure of capacity.
It is a decision, and its result will be counted in the dead.”
· exact text match
Why: The quote asserts that the outcome is a conscious decision and attaches moral weight to it, which is subjective framing beyond the reported data.
Claim: The article uses extreme, emotionally charged language to describe the response and its consequences.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: The phrase 'calculated and psychopathic social murder' is sensational, exceeding objective reporting and intended to provoke strong emotional reaction.
Claim: The article repeatedly prescribes specific political and economic actions as necessary solutions.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands and place them under its own democratic control.” · not found in supplied text
Why: The use of 'must' and the imperative prescription of a political program clearly show a prescriptive rather than descriptive stance.
Claim: The article criticizes military spending and advocates for reallocation to health, indicating a dovish stance.
“The United States found $87.6 billion for a military supplemental in a week but could not provide the mere $115 million for the WHO’s budget.” · exact text match
Why: This contrast criticizes military expenditures and implies a preference against hawkish priorities, but the dimension is not strongly developed.
Claim: The article emphasizes the worst-case projections and the response being outpaced, inducing fear.
“the outbreak continued to outpace the response” · exact text match
“worst-case scenario” · exact text match
Why: Combining 'outpaced' and 'worst-case scenario' amplifies the sense of danger and urgency, though it is fact-based.
Claim: The article is heavily opinionated, with explicit political analysis and calls to action.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: The strong moral condemnation is clearly opinion, not neutral fact-reporting.
Claim: The article is explicitly political, calling for a unified political struggle against imperialism.
“This requires a unified political struggle by workers in Africa, Europe and the Americas against the imperialist order that has organized global medicine around its own security, and the building of sections of the International Committee of the Fourth International.” · exact text match
Why: The direct call for a political struggle and reference to a specific political organization makes the article overtly political.
Claim: The article portrays the Congolese population and health workers as victims of systemic neglect.
“While Congolese doctors have been treating Ebola patients for two months without pay, Western governments flew their own nationals to hospitals in Frankfurt and Berlin.” · exact text match
Why: The contrast highlights victimization, but it is a factual comparison; the framing is only moderately victim-focused.
Claim: The article presents a coherent ideological framework (Marxist anti-imperialism) and applies it consistently.
“the imperialist order that has organized global medicine around its own security” · exact text match
Why: The phrase 'imperialist order' signals a consistent ideological lens applied to interpret the events.
Claim: The article is deeply critical of existing political, economic, and health institutions, framing them as complicit in preventable deaths.
“That is not a failure of capacity.
It is a decision, and its result will be counted in the dead.”
· exact text match
Why: The quote blames the outcome on a decision attributed to the institutional/systemic establishment, showing strong anti-establishment framing.
Claim: The article conveys strong negative emotions, particularly anger and condemnation.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: The language is morally charged and anger-inducing, indicating a negative emotional tone.
Claim: The article points out a double standard in treatment of Western nationals versus Congolese.
“While Congolese doctors have been treating Ebola patients for two months without pay, Western governments flew their own nationals to hospitals in Frankfurt and Berlin.” · exact text match
Why: The direct juxtaposition highlights an unequal application of resources and care, a clear double standard.
Claim: The article is strongly anti-corporate, criticizing pharmaceutical and biotechnology industries.
“answers to human need rather than to shareholder return” · exact text match
Why: The contrast between human need and shareholder return is explicitly anti-corporate.
Claim: The article advocates for collective ownership and democratic control, rejecting individualistic market solutions.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands and place them under its own democratic control.” · not found in supplied text
Why: The promotion of collective ownership and democratic control reflects a strong collectivist orientation.
Claim: The article uses emotionally manipulative language and selective framing to induce outrage.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: While the language is strong, it is based on factual underpinnings; the manipulation is moderate, as the core facts are not fabricated.
Claim: The article explicitly advocates Marxist class-based analysis and revolutionary action.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands” · exact text match
“the building of sections of the International Committee of the Fourth International” · exact text match
Why: These quotes directly invoke the working class, call for expropriation of private industry, and cite a Trotskyist international, unmistakably Marxist.
August 03, 2026 · 0 shares
Employs a Marxist anti-imperialist framing that attributes the outbreak's severity to capitalist and imperialist systems and prescribes working-class revolution and public ownership of health infrastructure.
Automated analysis; not human reviewed.
·
17 of 52 available dimensions scored; omitted dimensions are not treated as neutral.
·
Verified supporting quotes for 11 of 17 scored dimensions.
Claim: The article frames the outbreak severity and response failure as consequences of capitalism, imperialism, and private market priorities.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands and place them under its own democratic control, so that what gets developed answers to human need rather than to shareholder return and threat designation.” · exact text match
“Such actions define a calculated and psychopathic social murder: the foreseeable, documented and accepted killing of a population whose lives were weighed against procurement priorities and found to be worth less.” · exact text match
Why: These exact quotes explicitly attribute the lack of vaccines and inadequate response to capitalist/imperialist structures and call for working-class control, strongly indicating a far-left, anti-capitalist stance.
Claim: The article interjects strong moral judgments and subjective interpretations into what is otherwise a factual epidemiological report.
“That is not a failure of capacity.
It is a decision, and its result will be counted in the dead.”
· exact text match
Why: The quote asserts that the outcome is a conscious decision and attaches moral weight to it, which is subjective framing beyond the reported data.
Claim: The article uses extreme, emotionally charged language to describe the response and its consequences.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: The phrase 'calculated and psychopathic social murder' is sensational, exceeding objective reporting and intended to provoke strong emotional reaction.
Claim: The article repeatedly prescribes specific political and economic actions as necessary solutions.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands and place them under its own democratic control.” · not found in supplied text
Why: The use of 'must' and the imperative prescription of a political program clearly show a prescriptive rather than descriptive stance.
Claim: The article criticizes military spending and advocates for reallocation to health, indicating a dovish stance.
“The United States found $87.6 billion for a military supplemental in a week but could not provide the mere $115 million for the WHO’s budget.” · exact text match
Why: This contrast criticizes military expenditures and implies a preference against hawkish priorities, but the dimension is not strongly developed.
Claim: The article emphasizes the worst-case projections and the response being outpaced, inducing fear.
“the outbreak continued to outpace the response” · exact text match
“worst-case scenario” · exact text match
Why: Combining 'outpaced' and 'worst-case scenario' amplifies the sense of danger and urgency, though it is fact-based.
Claim: The article is heavily opinionated, with explicit political analysis and calls to action.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: The strong moral condemnation is clearly opinion, not neutral fact-reporting.
Claim: The article is explicitly political, calling for a unified political struggle against imperialism.
“This requires a unified political struggle by workers in Africa, Europe and the Americas against the imperialist order that has organized global medicine around its own security, and the building of sections of the International Committee of the Fourth International.” · exact text match
Why: The direct call for a political struggle and reference to a specific political organization makes the article overtly political.
Claim: The article portrays the Congolese population and health workers as victims of systemic neglect.
“While Congolese doctors have been treating Ebola patients for two months without pay, Western governments flew their own nationals to hospitals in Frankfurt and Berlin.” · exact text match
Why: The contrast highlights victimization, but it is a factual comparison; the framing is only moderately victim-focused.
Claim: The article presents a coherent ideological framework (Marxist anti-imperialism) and applies it consistently.
“the imperialist order that has organized global medicine around its own security” · exact text match
Why: The phrase 'imperialist order' signals a consistent ideological lens applied to interpret the events.
Claim: The article is deeply critical of existing political, economic, and health institutions, framing them as complicit in preventable deaths.
“That is not a failure of capacity.
It is a decision, and its result will be counted in the dead.”
· exact text match
Why: The quote blames the outcome on a decision attributed to the institutional/systemic establishment, showing strong anti-establishment framing.
Claim: The article conveys strong negative emotions, particularly anger and condemnation.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: The language is morally charged and anger-inducing, indicating a negative emotional tone.
Claim: The article points out a double standard in treatment of Western nationals versus Congolese.
“While Congolese doctors have been treating Ebola patients for two months without pay, Western governments flew their own nationals to hospitals in Frankfurt and Berlin.” · exact text match
Why: The direct juxtaposition highlights an unequal application of resources and care, a clear double standard.
Claim: The article is strongly anti-corporate, criticizing pharmaceutical and biotechnology industries.
“answers to human need rather than to shareholder return” · exact text match
Why: The contrast between human need and shareholder return is explicitly anti-corporate.
Claim: The article advocates for collective ownership and democratic control, rejecting individualistic market solutions.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands and place them under its own democratic control.” · not found in supplied text
Why: The promotion of collective ownership and democratic control reflects a strong collectivist orientation.
Claim: The article uses emotionally manipulative language and selective framing to induce outrage.
“Such actions define a calculated and psychopathic social murder.” · not found in supplied text
Why: While the language is strong, it is based on factual underpinnings; the manipulation is moderate, as the core facts are not fabricated.
Claim: The article explicitly advocates Marxist class-based analysis and revolutionary action.
“The international working class must take the pharmaceutical and biotechnology industries out of private hands” · exact text match
“the building of sections of the International Committee of the Fourth International” · exact text match
Why: These quotes directly invoke the working class, call for expropriation of private industry, and cite a Trotskyist international, unmistakably Marxist.

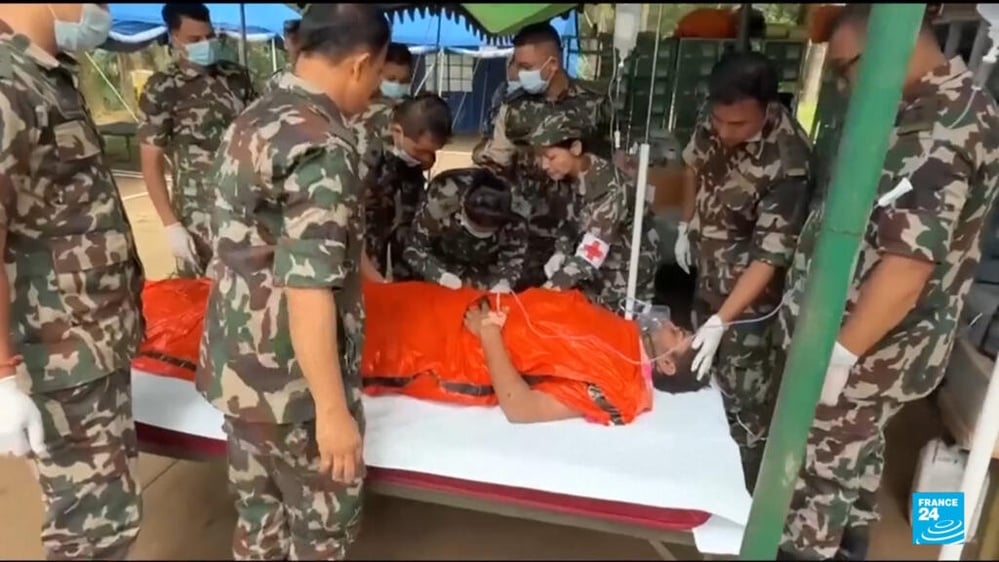
2026 © Helium Trades
Privacy Policy & Disclosure
* Disclaimer: Nothing on this website constitutes investment advice, performance data or any recommendation that any particular security, portfolio of securities, transaction or investment strategy is suitable for any specific person. Helium Trades is not responsible in any way for the accuracy
of any model predictions or price data. Any mention of a particular security and related prediction data is not a recommendation to buy or sell that security. Investments in securities involve the risk of loss. Past performance is no guarantee of future results. Helium Trades is not responsible for any of your investment decisions,
you should consult a financial expert before engaging in any transaction.
Helium Research Assistant

How can I help you today?
Ask any question about this page.


